

‘Getting harder to save’: The spiralling health of Rohingya children

23 Sep 2026

In the sprawling, overcrowded refugee camps of Cox’s Bazar, Bangladesh, a crisis far from the headlines is taking a severe toll on the youngest generation of Rohingya refugees. Children are arriving at medical facilities later, sicker, and with complex, overlapping physical and psychological health needs.

Nurses assist 10-day-old Aiyan Arfan

Nurse Jasmin Akter, supported by nurse Puja Dey, cares for 10-day-old Aiyan Arfan in the Paediatric Department of MSF’s Kutupalong Hospital. Aiyan is the son of 29-year-old Abul Hosen and 22-year-old Yasmin Fatema. Aiyan is their first child and suffered from fever and cough. He received respiratory support through a CPAP machine for his health condition. © Nazmul Islam/MSF

Nine years after fleeing extreme violence in Myanmar, children make up more than half of the 1.3 million refugees living in conditions of indefinite containment. In these camps, where international funding shrinks and is volatile, families struggle to secure basic food, healthcare, and education, placing children’s daily survival at constant risk.  

Beyond physical hardship, children and their families carry the heavy psychological weight of a life in limbo, trapped by political dynamics that fail to deliver meaningful solutions or ensure long-term safety and dignity. At Kutupalong Hospital - MSF’s largest hospital and main referral hub for people in the camps - medical teams are witnessing the largely overlooked impact of this crisis. What was once a hospital treating routine, seasonal illnesses has turned into an emergency facility managing children arriving in life-threatening conditions.

Previously, patients usually came in with a single illness and recovered well. Recently, however, children are arriving at our hospital later in the progression of their conditions, often with multiple illnesses and complications. This makes their clinical management much more challenging.

Dr Nadim Shahariyar
Deputy hospital director at Kutupalong Hospital

As primary health posts scale back due to drastic international funding cuts, secondary referral facilities like Kutupalong Hospital are left absorbing critical needs far beyond their original design. Today, severe physical disease, chronic malnutrition, and acute mental health distress are colliding, making children sicker and much harder to save.

Mina Bala sits with her two-month-old daughter, Misti Foti

Mina Bala sits with her two-month-old daughter, Misti Foti, at MSF’s Kutupalong Hospital. The infant was admitted with severe respiratory distress and is recovering well under the care of the medical team. © Nazmul Islam/MSF

Children admitted multiple times to Paediatrics

Inside the paediatric ward of Kutupalong Hospital, 25-year-old Yasmida sits at a hospital bed, holding her one-and-a-half-year-old daughter, Halima Sadia. Halima’s small body is fragile, weighed down by severe malnutrition, fever, and persistent infections that have left her too weak to sit or stand on her own. Yasmida fled Myanmar in 2017, surviving a treacherous 15-day journey across mountains and rivers to reach Bangladesh. Today, living in the camp with a family of seven, her daily reality is consumed by her child’s relentless cycles of illness - sometimes resulting in multiple hospital admissions in a single month.

“My baby has been very sick for many days now. Since her birth, we have frequented various hospitals and health facilities inside the camps around 10 to 12 times, and she was admitted to the MSF hospital four times,” Yasmida shares.

Yasmida’s experience navigating health emergencies in the middle of the night reflects the severe security and logistical barriers families face in the camps. “Stepping out in the camp at night is terrifying because it is very dark, and I feel scared. Once at 2:00 AM, my daughter became extremely ill. As my husband and I set off toward the hospital with our sick baby, after walking a short distance, we came across a group of men. They beat up my husband and looted everything he had. Frightened that night, we returned home in that condition with our daughter and only took her to the doctor the next morning. Because of these things, if the child falls ill at night, we cannot go out, and her health worsens further due to not receiving timely treatment.” 

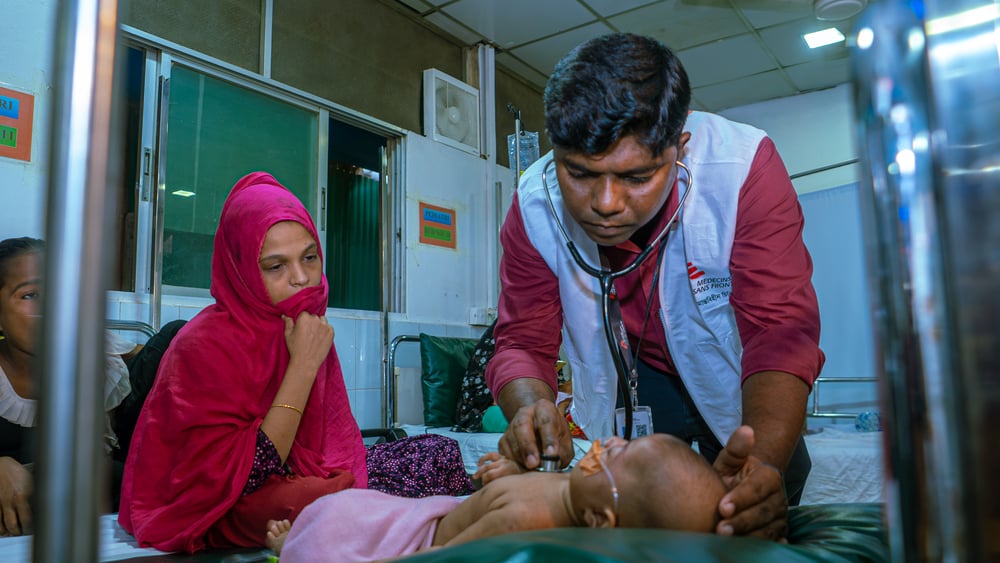
Dr Nadim Shahariyar checks on Aiyan Arfan

Dr Nadim Shahariyar, deputy hospital director of MSF’s Kutupalong Hospital, visited the Paediatric Department and followed up on the condition of Aiyan Arfan who was critically ill. He spoke with Aiyan’s family about his condition and the next steps in his treatment process. © Nazmul Islam/MSF

This delay in seeking care echoes across the camps. Dr Nadim Shahariyar, deputy hospital director at Kutupalong Hospital, observes that Yasmida and Halima’s story is part of a broader trend. “Over the last few years, we have seen significant changes in paediatric admissions to our hospital. One thing we know for sure is that patients are arriving in more critical condition and with multiple illnesses at the same time,” says Dr Nadim. “Previously, patients usually came in with a single illness and recovered well. Recently, however, children are arriving at our hospital later in the progression of their conditions, often with multiple illnesses and complications. This makes their clinical management much more challenging.”

Dr Nadim highlights how drastic cuts to humanitarian aid have forced families into desperate daily trade-offs that directly delay medical care:  

“Within the camps, we have observed a significant reduction in funding. As a result, families are struggling to meet their basic daily needs. When parents are forced to prioritise daily survival - like securing food or safety - they delay seeking hospital care for a sick child until it becomes a life-threatening emergency, leading to an influx of far more severe cases. It is particularly difficult for a child to recover when their immune system is compromised, whether by malnutrition or other diseases. Recovery can be extremely difficult, and despite treatment, the outcomes are not always successful. Malnutrition acts as an invisible amplifier, turning treatable childhood infections into life-threatening emergencies.”

Stepping out in the camp at night is terrifying because it is very dark, and I feel scared... Because of these things, if the child falls ill at night, we cannot go out, and her health worsens further due to not receiving timely treatment.

Yasmida
A 25-year-old Rohingya refugee whose one-and-a-half-year-old daughter, Halima has been impacted by severe malnutrition, fever, and persistent infections

A tipping point for adolescent wellbeing  

Beyond physical illness, a mental health emergency is taking a devastating toll on young people. Chronic stress, severe poverty, lack of educational opportunities, and exposure to family disputes are driving a sharp rise in adolescent distress. Thirteen-year-old Beauty and 14-year-old Jasmine both reached a breaking point inside their overcrowded shelters, leading to suicide attempts before receiving psychiatric care and counselling at MSF’s Shantikhana, a mental health counselling room and safe space at the facility.  

“With the rations we receive, we somehow get by eating just rice and lentils. We cannot eat anything beyond that. Driven by so much suffering and deprivation, I made that decision,” recalls Beauty, who attempted suicide following severe food scarcity and family conflict. “After this incident, I came to Shantikhana. A counsellor explained things to me and provided counselling. I now understand that dying is not a solution.”

Rohingya children Taslima and Jannatul Ferdous playing together

Rohingya children Taslima and Jannatul Ferdous play together in the designated children’s play area of the Mental Health Department at MSF Kutupalong Hospital. © Nazmul Islam/MSF

“Life in the camp is difficult for people our age,” Jasmine explains, sharing how systemic hardship exacerbates tension at home. “The living conditions here are not good. Many people are crammed into small shelters, and families have barely any income, which causes a lot of distress. Overall, life here is barely manageable. If only the environment in the camp were better, perhaps we would feel better.”  

The painful experiences of Beauty and Jasmine reflect stark admission trends recorded at Kutupalong Hospital. Facility-based data between 2023 and 2025 reveals that children under 18 years of age accounted for 27 per cent (160 out of 586) of all recorded suicide attempts, meaning one in every four attempts was a child. Over the same period, 81 per cent of these paediatric suicide attempts were directly attributed to family violence, exacerbated by severe crowding and relentless daily stress. This crisis is growing rapidly, with the proportion of children under 15 seeking MSF mental health support jumping from 9.7 per cent (131 cases) in 2021 to 29.4 per cent (232 cases) in 2025.

Shariful Islam, MSF’s mental health activity manager, emphasises that these acts are clear cries for help in an unviable environment. “We are observing that both the volume of mental health patients and the severity of their conditions have increased significantly compared to five years ago. Our team also observes that suicide attempts are driven by a complex interplay of factors rather than a single isolated cause. The root drivers stem from inadequate humanitarian assistance, lack of freedom of movement, and a pervasive loss of hope after nearly nine years of displacement.”

Social worker Fatema Jinnat Laboni applies henna to a patient as part of a psychosocial session

At the MSF mental health department in Kutupalong Hospital, social worker Fatema Jinnat Laboni and counsellor educator Rozina Akter facilitate a psychosocial support session. Using activities like applying henna, the team fosters an informal environment that helps them build trust, listen to patient experiences, and better understand their psychosocial needs. © Nazmul Islam/MSF

Beyond emergency response: An urgent call for systemic solutions  

The findings from Kutupalong Hospital demonstrate that paediatric illness and rising child mental health distress are not isolated medical issues, but indicators of a broader protection and public health emergency. Reduced funding across the camps has crippled primary healthcare, compromised nutrition programs, and eroded basic living conditions - forcing secondary facilities like Kutupalong Hospital to absorb critical needs far beyond their original design.  

A malnourished child with pneumonia, a young person in acute psychological distress, or a patient whose chronic condition is no longer controlled may appear as isolated medical emergencies. But together, they reveal the devastating health consequences of a system steadily contracting around a confined population.  

Emergency medical intervention cannot substitute for political responsibility -humanitarian and health actors, alongside international stakeholders, must sustain an adequate humanitarian response, ensuring that basic food, healthcare, and protection are reinforced while a lasting political solution is sought.

